Tag: Infectious Diseases

  • CAD alone outperformed CAD-plus-CRP tuberculosis screening

    What the study found

    Computer-aided detection (CAD) software used on digital chest X-rays alone found more tuberculosis cases and cost less than CAD followed by C-reactive protein (CRP, a blood test that can indicate inflammation) testing. The combined approach did not meet the study's non-inferiority criterion.

    Why the authors say this matters

    The authors conclude that, in community active tuberculosis case-finding, CAD followed by CRP offered no advantage over CAD alone because it had lower case yield and higher cost. They also suggest that CAD alone could be an effective and economically viable screening strategy in high-burden areas.

    What the researchers tested

    This pragmatic community trial with a paired screen-positive design compared two screening approaches within the same participants. Adults in households in Butha-Buthe District, Lesotho, and uMgungundlovu District, South Africa, were screened using CAD4TBv7 alone or CAD4TBv7 followed by CRP testing when the CAD score fell in a specified range, with confirmatory Xpert MTB/RIF Ultra testing when required.

    What worked and what didn't

    Among 20,023 enrolled participants, the primary outcome set included 73 people with tuberculosis identified by at least one approach and complete data for both. CAD4TBv7 identified 69 of these cases (94.5%), while CAD4TBv7-CRP identified 60 (82.2%); the difference was -12.3%, so the non-inferiority criterion was not met. The cost per detected tuberculosis case was US$5,454 for CAD4TBv7 and US$7,486 for CAD4TBv7-CRP, making the combined approach 37.3% more expensive.

    What to keep in mind

    The comparison was limited to the study's community setting in two districts and to the participants who met eligibility criteria. The abstract does not describe additional limitations beyond the non-inferiority failure and the cost difference.

    • CAD alone detected 69 of 73 tuberculosis cases in the primary outcome set.
    • CAD followed by CRP detected 60 of 73 cases and did not meet non-inferiority.
    • The combined CAD-CRP approach cost more per detected case than CAD alone.
    • The study enrolled 20,023 adults from community settings in Lesotho and South Africa.
    • The authors conclude that CAD alone may be a viable screening strategy in high-burden settings.
  • Biopsy confirmed isolated central nervous system tuberculosis in progressive encephalopathy

    What the study found

    The report describes a biopsy-proven case of isolated central nervous system tuberculosis (TB) in a 76-year-old woman with progressive encephalopathy. The diagnosis was confirmed only after an open meningeal biopsy showed necrotizing granulomas with acid-fast bacilli.

    Why the authors say this matters

    The authors conclude that central nervous system TB can be difficult to recognize because its clinical and radiologic features are often nonspecific and can resemble malignancy, inflammatory disorders, or fungal infections. They also state that early recognition is important for timely treatment and improved neurologic outcomes.

    What the researchers tested

    This is a case report of one patient who presented after travel to Ghana with a six-month history of progressive encephalopathy. The evaluation included cerebrospinal fluid testing, neuroimaging, empiric antituberculous therapy, and an open meningeal biopsy for definitive diagnosis.

    What worked and what didn't

    Initial neuroimaging was unrevealing, and routine meningitis testing was negative. Cerebrospinal fluid analysis showed lymphocytic pleocytosis and markedly low glucose, later brain magnetic resonance imaging showed diffuse nodular leptomeningeal enhancement, and the patient improved clinically and radiologically with antituberculous therapy and adjunctive corticosteroids.

    What to keep in mind

    The available summary describes a single patient, so the findings are limited to this case. The abstract also notes that conventional cerebrospinal fluid testing has limited sensitivity and that no evidence of pulmonary TB was identified in this patient.

    • A 76-year-old woman was diagnosed with isolated central nervous system TB after open meningeal biopsy.
    • Her presentation included six months of progressive encephalopathy after travel to Ghana.
    • Routine meningitis testing was negative, and the first neuroimaging study was unrevealing.
    • Cerebrospinal fluid showed lymphocytic pleocytosis and very low glucose.
    • Brain MRI later showed diffuse nodular leptomeningeal enhancement involving the posterior fossa and brainstem.
    • The patient improved with antituberculous therapy and adjunctive corticosteroids.
  • Abstract discusses pediatric tuberculosis care, not an isoniazid dose revision

    What the study found

    The abstract does not present a study finding about whether the dose of isoniazid, a tuberculosis medicine, should be revised for children. Instead, it summarizes broader problems in childhood tuberculosis care, including low case notification and diagnostic difficulties.

    Why the authors say this matters

    The authors note that early diagnosis and treatment are central to addressing childhood tuberculosis, and they point to the need for better care systems and diagnostic tools. They also mention that the World Health Organization has developed treatment algorithms and a clinical standard to support healthcare workers caring for children and adolescents with tuberculosis.

    What the researchers tested

    No research methods or study design are described in the abstract provided. The text reads as a brief commentary or overview rather than as a report of an experiment or clinical study.

    What worked and what didn't

    The abstract reports that tuberculosis affects around 1.25 million children each year and that case notification is about 55% in children, lower than in adults. It also states that children often cannot produce sputum samples, have paucibacillary disease (a form of disease with few bacteria), and face limited access to radiology in resource-limited settings, which complicates diagnosis and care.

    What to keep in mind

    The abstract does not provide a direct answer to the title's question about revising isoniazid dose in children. It also does not describe study design, data, outcomes, or limitations beyond the general challenges in pediatric tuberculosis care.

    • The abstract does not report a specific finding on isoniazid dosing in children.
    • It says childhood tuberculosis care is complicated by diagnostic difficulties and low case notification.
    • Children may be hard to diagnose because they often cannot produce sputum samples and may have paucibacillary disease.
    • The authors mention WHO treatment algorithms and a clinical standard developed to support care.
    • The text provides no study methods or direct results for a dosing revision question.
  • Nine-month all-oral tuberculosis regimens showed durable three-year outcomes

    What the study found

    The study found that nine-month, all-oral regimens for rifampicin-resistant tuberculosis were associated with durable outcomes three years after treatment ended. Persistent linezolid-related neuropathic or visual symptoms were also still seen in a substantial share of participants.

    Why the authors say this matters

    The authors conclude that the findings support durable three-year outcomes for these regimens. They also say the persistent neuropathy warrants proactive mitigation, including reducing cumulative linezolid exposure or using linezolid-sparing alternatives when feasible.

    What the researchers tested

    This was a multicentre, prospective cohort study in China called MDR-Chin. It included 124 adults with culture-confirmed multidrug-resistant or rifampicin-resistant tuberculosis, or pre-extensively drug-resistant tuberculosis, who received one of four nine-month all-oral regimens containing linezolid at 600 mg/day. The researchers assessed efficacy 36 months after treatment completion and tracked persistent linezolid-related neuropathic or visual symptoms lasting at least 24 months.

    What worked and what didn't

    At 36 months after treatment completion, 111 of 124 participants, or 89.5%, had a favourable outcome, defined as no failure, relapse, or death. There were no significant differences in favourable outcomes among the four regimens. Persistent linezolid-related neuropathic or visual symptoms were reported by 28 of 124 participants, or 22.6%, and foot numbness was the most frequent symptom, reported by 22 participants.

    What to keep in mind

    The study was non-randomised and observational, so it does not establish causal comparisons between regimens. The abstract does not provide further detail on the causes of symptoms beyond linezolid-related neuropathic or visual effects, and it does not describe additional limitations.

    • 111 of 124 participants had a favourable outcome 36 months after treatment ended.
    • No significant differences in favourable outcomes were seen among the four regimens.
    • 28 of 124 participants reported persistent linezolid-related neuropathic or visual symptoms.
    • Foot numbness was the most common persistent symptom.
    • The authors suggest reducing cumulative linezolid exposure or using linezolid-sparing alternatives when feasible.
  • CBC-derived ratios show limited diagnostic value in rheumatic disease tuberculosis

    What the study found

    The study found that complete blood cell count-derived ratios, including the platelet-to-lymphocyte ratio (PLR), monocyte-to-lymphocyte ratio (MLR), and neutrophil-to-lymphocyte ratio (NLR), were higher in people with active tuberculosis. In people with rheumatic diseases, these measures had limited standalone value for diagnosing active tuberculosis, but they may help with risk stratification.

    Why the authors say this matters

    The authors say these ratios should be considered complementary tools, not replacements, for microbiological tests, because active tuberculosis often relies on clinical diagnosis when microbiologic testing has limited sensitivity. They also suggest these measures may be useful in resource-limited settings or to prompt further definitive testing.

    What the researchers tested

    The researchers enrolled 305 people with active tuberculosis and 171 healthy controls to evaluate diagnostic performance of CBC-derived ratios using receiver operating characteristic curves. They also validated the findings in a multi-center rheumatic disease cohort and used a nested case-control study to examine whether these ratios were linked to later development of active tuberculosis.

    What worked and what didn't

    Platelet, monocyte, and neutrophil counts increased, while lymphocyte count decreased, in people with active tuberculosis compared with healthy controls. PLR, MLR, and NLR were elevated, and the combination of monocyte count, PLR, and NLR showed good diagnostic efficiency with an area under the curve of 0.916; after anti-tuberculosis treatment, these indices were restored. In the rheumatic disease population, however, diagnostic efficiency was limited, with an area under the curve of 0.637, although PLR at or above 130.27 was associated with a higher one-year risk of developing active tuberculosis.

    What to keep in mind

    The abstract does not provide detailed limitations beyond noting limited standalone diagnostic value in rheumatic disease populations. The findings are presented within the studied groups and should not be taken as evidence that these ratios can replace microbiological testing.

    • PLR, MLR, and NLR were higher in people with active tuberculosis than in healthy controls.
    • A combination of monocyte count, PLR, and NLR had good diagnostic performance for active tuberculosis (AUC = 0.916).
    • In people with rheumatic diseases, CBC-derived ratios had limited standalone diagnostic value for active tuberculosis (AUC = 0.637).
    • PLR at or above 130.27 was associated with a higher one-year risk of developing active tuberculosis in the rheumatic disease cohort.
    • The authors describe these ratios as complementary tools rather than replacements for microbiological tests.
  • Short-course anti-TB therapy preceded regression of a reactivated tuberculous focus

    What the study found

    In this case, a previously stable pulmonary tuberculous focus reactivated after chemoimmunotherapy with tislelizumab, and it later regressed even though the patient did not complete a full anti-tuberculosis course. The patient then continued tislelizumab maintenance, and both the cancer lesion and the tuberculous lesion were stable at 10 months.

    Why the authors say this matters

    The authors conclude that a short course of anti-tuberculosis therapy may be a viable management strategy for immune checkpoint inhibitor (ICI, immune checkpoint inhibitor)–induced reactivation of a stable tuberculosis focus. They suggest this may help patients continue ICIs safely and may challenge the usual requirement for a complete anti-TB course in this specific situation.

    What the researchers tested

    This is a case report of a 69-year-old man with stage IV lung squamous cell carcinoma and a long-term radiologically stable, untreated pulmonary tuberculous focus. He received paclitaxel, carboplatin, and tislelizumab, and the reactivated tuberculous lesion was confirmed by next-generation sequencing.

    What worked and what didn't

    The malignant mass regressed after four cycles of chemoimmunotherapy. The previously stable tuberculous focus reactivated, and anti-tuberculosis treatment was stopped by the patient after two months because of severe synergistic toxicity with chemotherapy; after that, the granulomatous lesion regressed to its original baseline size.

    What to keep in mind

    This is a single case report, so the findings are limited to one patient. The abstract does not describe broader testing, and it does not provide a general treatment rule beyond this specific scenario.

    • A stable pulmonary tuberculous focus reactivated after treatment with paclitaxel, carboplatin, and tislelizumab.
    • The tuberculous reactivation was confirmed by next-generation sequencing.
    • The patient stopped anti-tuberculosis therapy after two months because of severe synergistic toxicity with chemotherapy.
    • The reactivated granulomatous lesion regressed back to baseline size without a full anti-TB course.
    • At 10 months, both the tuberculosis lesion and the cancer lesion were stable while tislelizumab maintenance continued.
  • Most patients with trace Ultra results were advised to receive TB treatment

    What the study found

    The study found that trace-positive sputum results on Xpert MTB/RIF Ultra were not always linked to tuberculosis (TB) disease. In two high-burden clinical settings, about half of the participants with these trace results were recommended TB treatment, while a smaller group had microbiologically confirmed TB.

    Why the authors say this matters

    The authors conclude that this prevalence supports treating most people with trace sputum results when multimodal testing and repeated clinical evaluations are not feasible. They also suggest that people with low-risk characteristics and negative results on other widely available tests may be able to defer treatment with clinical follow-up.

    What the researchers tested

    The researchers enrolled adults and adolescents with trace-positive sputum results during initial TB evaluation in Uganda and South Africa. Participants were evaluated at enrollment, and those with uncertain TB status were followed off treatment for up to 3 months with repeat assessments by TB clinicians.

    What worked and what didn't

    TB was identified by sputum culture at enrollment in 20% of the 311 participants. Within 3 months, 48% were judged to warrant TB treatment, and among those followed to microbiologic outcomes, 30% had positive culture and 41% had positive culture or Ultra; two participants died. Having TB symptoms, advanced HIV, and no recent TB history were associated with microbiologically confirmed TB disease, and an abnormal chest X-ray or elevated C-reactive protein was also associated in some groups.

    What to keep in mind

    The study was done in two high-burden clinical settings, so the findings may not apply everywhere. The abstract also notes that some outcomes were based on clinical judgment and follow-up, and it does not describe detailed limitations beyond the available follow-up and testing approach.

    • Trace-positive Ultra results did not always mean TB disease.
    • TB culture at enrollment was positive in 20% of participants.
    • Nearly half of participants were recommended TB treatment within 3 months.
    • TB symptoms, advanced HIV, and no recent TB history were linked to confirmed TB.
    • Some participants with low-risk features and negative other tests may defer treatment with follow-up.
  • tNGS showed high accuracy for non-sputum tuberculosis detection

    tNGS showed high accuracy for non-sputum tuberculosis detection

    What the study found

    The study found that nanopore-based targeted next-generation sequencing, or tNGS, had high accuracy for detecting tuberculosis in non-sputum specimens and for identifying several drug resistance patterns. The authors also reported that its performance was especially notable in patients with low bacterial loads.

    Why the authors say this matters

    The authors say this matters because tuberculosis diagnosis is still difficult, especially for people who cannot provide sputum. They conclude that tNGS may be an alternative method for diagnosing non-sputum tuberculosis patients and for producing drug-resistance profiles.

    What the researchers tested

    The researchers ran a multicenter prospective lab-developed study in five tuberculosis hospitals in China and enrolled 701 participants. They tested non-sputum specimens with tNGS, Xpert Mycobacterium tuberculosis/RIF, and culture, then compared tNGS against the microbiological reference standard. They also used phenotypic drug susceptibility testing on culture-positive isolates to assess drug-resistance detection.

    What worked and what didn't

    Using the microbiological reference standard, tNGS had sensitivity of 93.4% and specificity of 93.2% for tuberculosis detection. The diagnostic performance was reported as robust across specimen types and clinical symptoms, and more than 90% of tNGS-positive individuals obtained drug susceptibility results, which were mainly dependent on bacterial loads. tNGS also showed high sensitivity and specificity for rifampicin, isoniazid, streptomycin, ethambutol, and levofloxacin resistance, and it had potential to detect other coinfecting respiratory pathogens.

    What to keep in mind

    The abstract does not describe detailed limitations beyond noting that drug susceptibility results were mainly dependent on bacterial loads. The findings come from non-sputum specimens collected in five designated tuberculosis hospitals in China, so the available summary does not state how well the assay performs outside that setting.

    • tNGS detected tuberculosis in non-sputum specimens with 93.4% sensitivity and 93.2% specificity.
    • The assay’s performance was reported to be robust across specimen types and clinical symptoms.
    • More than 90% of tNGS-positive participants received drug susceptibility results.
    • tNGS showed high performance for resistance to rifampicin, isoniazid, streptomycin, ethambutol, and levofloxacin.
    • The authors say the assay may be an alternative for diagnosing non-sputum tuberculosis patients.
  • Machine learning models identified key drivers of tuberculosis incidence in Taiwan

    What the study found

    The study found that several machine learning and deep learning models could forecast monthly tuberculosis incidence across 19 cities and counties in Taiwan, China, and that the CatBoost, random forest, and gradient boosting models performed best. The authors also identified population size, sulfur dioxide levels, physician count, normalized difference vegetation index, wind velocity, and precipitation as the main influences on tuberculosis incidence.

    Why the authors say this matters

    The authors conclude that the framework and findings provide data support and a decision-making basis for tuberculosis mitigation initiatives on a global scale. The study suggests that identifying influential factors and their thresholds may help guide tuberculosis-related decision-making.

    What the researchers tested

    The researchers analyzed data from 19 cities and counties in Taiwan, China from 2014 to 2022. They used four machine learning models and four deep learning models, along with 12 drivers, to predict monthly tuberculosis incidence, and then applied post-hoc explainable machine learning techniques, stepwise regression, and statistical assessments.

    What worked and what didn't

    CatBoost, random forest, and gradient boosting emerged as the top-performing models. The study also reported nonlinear interactions and threshold effects between the identified determinants and tuberculosis incidence, and it used stepwise regression to find a model configuration that reduced the number of drivers while keeping high predictive accuracy.

    What to keep in mind

    The abstract does not describe detailed performance values, specific limitations, or uncertainty measures. It also focuses on Taiwan, China, so the scope described in the summary is geographically specific.

    • The study used data from 19 cities and counties in Taiwan, China between 2014 and 2022.
    • CatBoost, random forest, and gradient boosting were the best-performing models.
    • Population size, sulfur dioxide, physician count, vegetation index, wind velocity, and precipitation were identified as the main influences on tuberculosis incidence.
    • The authors reported nonlinear interactions and threshold effects between these factors and tuberculosis incidence.
    • Stepwise regression was used to reduce the number of drivers while keeping high predictive accuracy.
  • Isoniazid-related hair loss occurred with isoniazid monoresistant tuberculosis

    Isoniazid-related hair loss occurred with isoniazid monoresistant tuberculosis

    What the study found

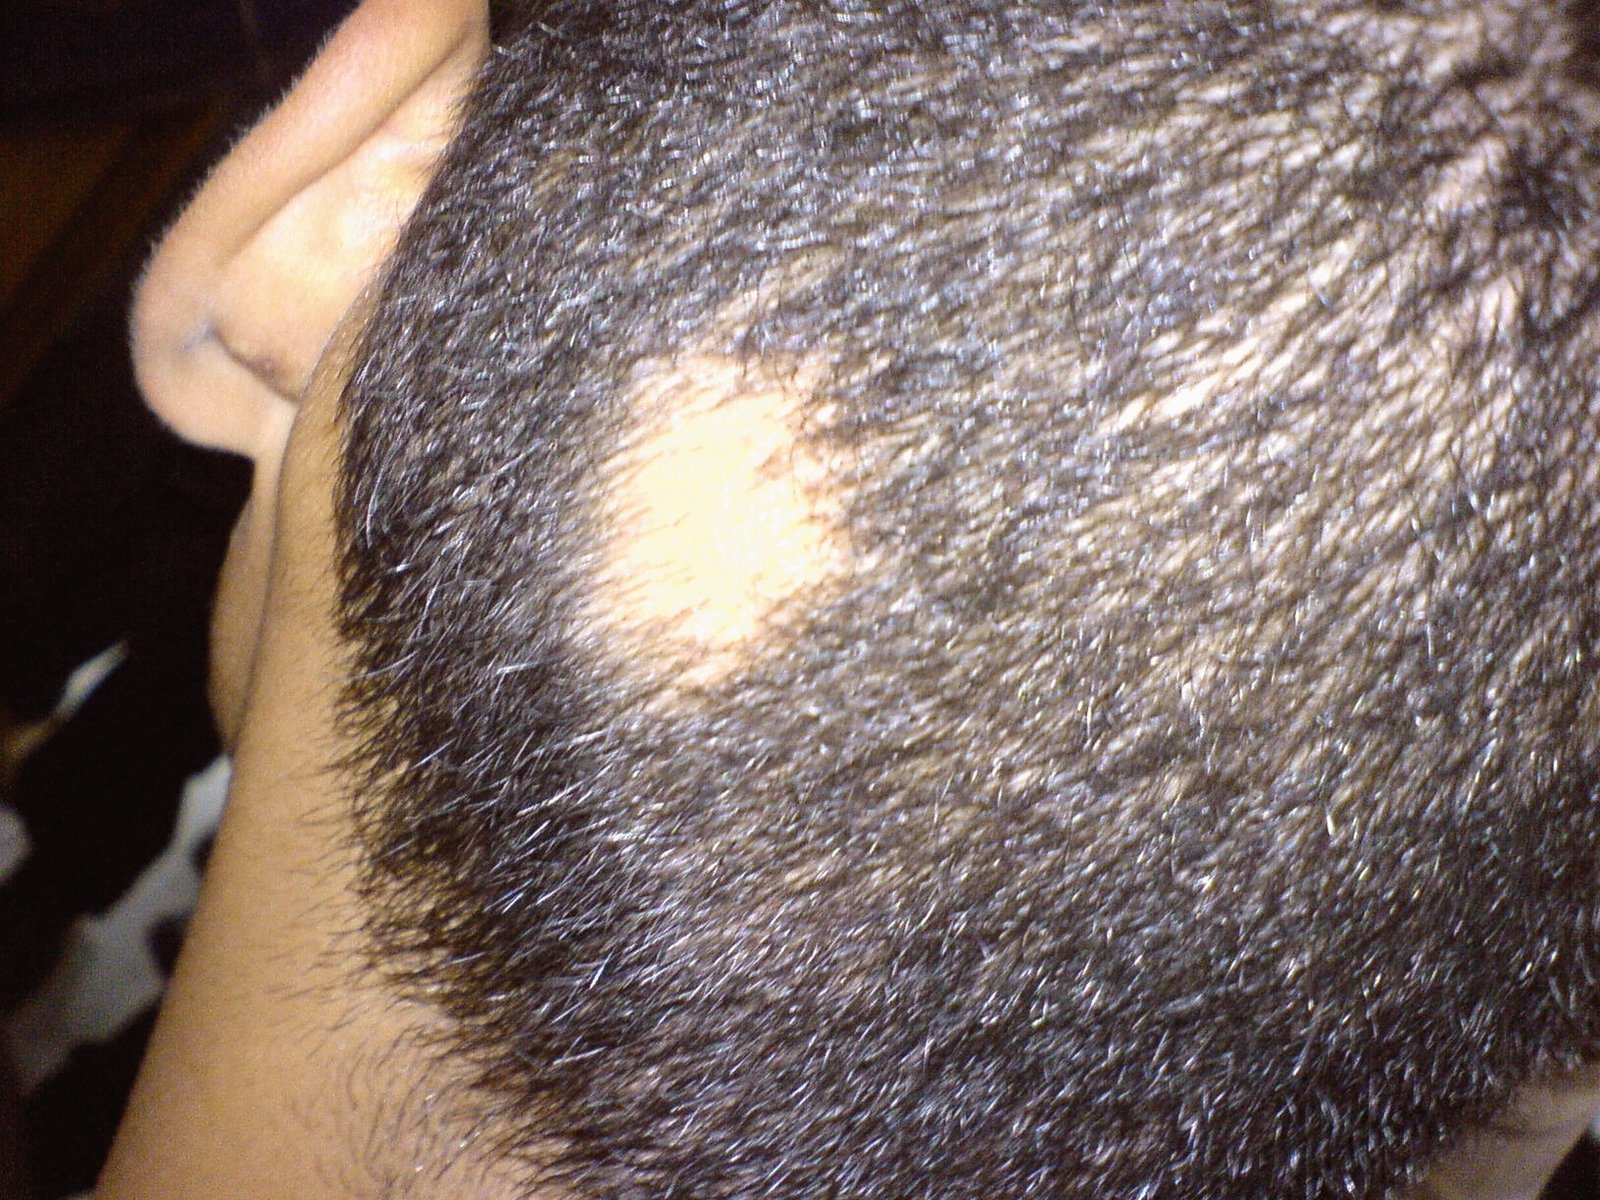
    The report describes a 22-year-old woman with pulmonary tuberculosis who developed sudden, severe alopecia, meaning hair loss, after starting antituberculosis treatment. Isoniazid was stopped, her hair began to regrow within 1 month, and later testing showed that her tuberculosis was resistant to isoniazid alone.

    Why the authors say this matters

    The authors conclude that clinicians should watch for alopecia in young female patients receiving antituberculosis treatment, because it may lead to treatment interruption for cosmetic reasons. They also suggest that alopecia may signal underlying drug resistance, although they say more studies are needed to establish biological evidence for this association.

    What the researchers tested

    This was a case report of one patient. The researchers described the patient's tuberculosis treatment, the timing of hair loss, the decision to stop isoniazid, the return of hair growth, and the results of drug resistance testing.

    What worked and what didn't

    After isoniazid was discontinued, hair regrowth was observed within 1 month. Drug resistance testing then revealed isoniazid monoresistance, meaning resistance to isoniazid alone, and treatment continued with rifampicin, pyrazinamide, ethambutol, and moxifloxacin for 2 months, followed by rifampicin and ethambutol for 7 months.

    What to keep in mind

    This summary is based on a single case, so it cannot show how often this happens or prove a general cause-and-effect relationship. The abstract also states that further studies are needed to establish biological evidence for the suggested link between alopecia and drug resistance.

    • A 22-year-old woman with pulmonary tuberculosis developed sudden, severe hair loss after starting treatment.
    • Isoniazid was suspected, stopped, and hair regrowth was seen within 1 month.
    • Testing later showed isoniazid monoresistance.
    • The authors say alopecia may lead to treatment interruption for cosmetic reasons.
    • The abstract says more studies are needed to confirm any biological link between alopecia and drug resistance.